Your correspondent had the privilege of discussing HK property outlook during an RTHK evening live programme.
2020年11月6日星期五

2020年10月22日星期四
3 more important links - False Positives in covid tests, and Frontline Doctors speaking out again
"Of all tyrannies, a tyranny sincerely exercised for the good of its victims may be the most oppressive. It would be better to live under robber barons than under omnipotent moral busybodies. The robber baron's cruelty may sometimes sleep, his cupidity may at some point be satiated; but those who torment us for our own good will torment us without end for they do so with the approval of their own conscience. " --- C. S. Lewis
We continue to bring you alternative views that contradict the mainstream narrative - hopefully independent minded readers can make a more balanced assessment of where the real threat lies.
1) We Are No Longer In A Pandemic. Netherlands fighting back!
Below is a briefing by World Doctors Alliance
where an "Open letter to the UK Government, Governments of the World and the Citizens of the World" has a lot more details.
As of, 22.10.2020, total signatures numbered: 20,831, of which
General public: 17,986
Doctors, nurses, scientists, dentists, etc: 1,254
Holistic health practitioners: 1,591
Video here:
2) Lies, Damned Lies and Health Statistics – The Deadly Danger of False Positives
by Dr. Mike Yeadon
Dr. Mike Yeadon, a former Vice President and Chief Science Officer for Pfizer for 16 years, says that half or even "almost all" of tests for COVID are false positives. Dr. Yeadon also argues that the threshold for herd immunity may be much lower than previously thought, and may have been reached in many countries already.
Highlights from his article:
- test cannot distinguish between a living virus and a short strand of RNA from a virus which broke into pieces weeks or months ago.
- Because of the high false positive rate and the low prevalence, almost every positive test, a so-called case, identified by Pillar 2 since May of this year has been a FALSE POSITIVE. Not just a few percent. Not a quarter or even a half of the positives are FALSE, but around 90% of them.
- The test exaggerates the number of covid-19 cases by almost ten-fold... This test is fatally flawed and MUST immediately be withdrawn and never used again
- The likelihood of an apparently positive case being a false positive is between 89-94%, or near-certainty.
3) America's Frontline Doctors: White Coat Summit II - SCOTUS Press Conference
There are plenty of gems to quote but just some quick bites:
- We exist to counter the massive disinformation campaign regarding the pandemic.
- We are diverse, exceedingly well-credentialed physicians, with extensive front line experience treating both COVID-19 and the risky health effects due to the lockdowns. There are many early treatment options! Most people do just fine!
- Unlike the government, CDC, FDA, NIH or any other organization with other motives, we doctors have a fiduciary, moral, ethical, legal and spiritual obligation to help people … and that means you. We are not the media. Please share widely.
see the press conference clip here:
https://www.bitchute.com/video/4BaCzHJgSHTX/
If you missed earlier coverage on the first summit of the America's Frontline Doctors, see this:
https://www.bitchute.com/video/U9AUUOUav46o/
And how the first summit was censored by Youtube:
2020年10月14日星期三
3 charts/table on lockdowns
1) the more daconian the lockdown, the more deaths?


2020年10月12日星期一
Scientists against lockdown/vaccine - 5 recent references
1) scientists call for end to lockdowns
if you are still waiting for more scientific proof that the covid is no more harmful than normal flu, here are 15,000 more pieces of them... so see below, and spread the message if you are getting sick staying home, or losing job because your employer is slashing staff or even going bust, etc. etc...
do you believe a few govt mouthpiece 'scientists' or the independent scientific community at large?
Signed by
Medical & Public
Health Scientists
5,204
Medical
Practitioners
10,231
General
Public
140,605
The Great Barrington Declaration
As infectious disease epidemiologists and public health scientists we have grave concerns about the damaging physical and mental health impacts of the prevailing COVID-19 policies, and recommend an approach we call Focused Protection.
Coming from both the left and right, and around the world, we have devoted our careers to protecting people. Current lockdown policies are producing devastating effects on short and long-term public health. The results (to name a few) include lower childhood vaccination rates, worsening cardiovascular disease outcomes, fewer cancer screenings and deteriorating mental health – leading to greater excess mortality in years to come, with the working class and younger members of society carrying the heaviest burden. Keeping students out of school is a grave injustice.
Keeping these measures in place until a vaccine is available will cause irreparable damage, with the underprivileged disproportionately harmed.
Fortunately, our understanding of the virus is growing. We know that vulnerability to death from COVID-19 is more than a thousand-fold higher in the old and infirm than the young. Indeed, for children, COVID-19 is less dangerous than many other harms, including influenza.
As immunity builds in the population, the risk of infection to all – including the vulnerable – falls. We know that all populations will eventually reach herd immunity – i.e. the point at which the rate of new infections is stable – and that this can be assisted by (but is not dependent upon) a vaccine. Our goal should therefore be to minimize mortality and social harm until we reach herd immunity.
The most compassionate approach that balances the risks and benefits of reaching herd immunity, is to allow those who are at minimal risk of death to live their lives normally to build up immunity to the virus through natural infection, while better protecting those who are at highest risk. We call this Focused Protection.
Adopting measures to protect the vulnerable should be the central aim of public health responses to COVID-19. By way of example, nursing homes should use staff with acquired immunity and perform frequent PCR testing of other staff and all visitors. Staff rotation should be minimized. Retired people living at home should have groceries and other essentials delivered to their home. When possible, they should meet family members outside rather than inside. A comprehensive and detailed list of measures, including approaches to multi-generational households, can be implemented, and is well within the scope and capability of public health professionals.
Those who are not vulnerable should immediately be allowed to resume life as normal. Simple hygiene measures, such as hand washing and staying home when sick should be practiced by everyone to reduce the herd immunity threshold. Schools and universities should be open for in-person teaching. Extracurricular activities, such as sports, should be resumed. Young low-risk adults should work normally, rather than from home. Restaurants and other businesses should open. Arts, music, sport and other cultural activities should resume. People who are more at risk may participate if they wish, while society as a whole enjoys the protection conferred upon the vulnerable by those who have built up herd immunity.
On October 4, 2020, this declaration was authored and signed in Great Barrington, United States, by:
Dr. Martin Kulldorff, professor of medicine at Harvard University, a biostatistician, and epidemiologist with expertise in detecting and monitoring of infectious disease outbreaks and vaccine safety evaluations.
Dr. Sunetra Gupta, professor at Oxford University, an epidemiologist with expertise in immunology, vaccine development, and mathematical modeling of infectious diseases.
Dr. Jay Bhattacharya, professor at Stanford University Medical School, a physician, epidemiologist, health economist, and public health policy expert focusing on infectious diseases and vulnerable populations.
Co-signers
Medical and Public Health Scientists and Medical Practitioners
Dr. Sucharit Bhakdi, physician and professor emeritus of medical microbiology, University of Mainz, Germany
Dr. Rajiv Bhatia, physician, epidemiologist and public policy expert at the Veterans Administration, USA
Dr. Stephen Bremner,professor of medical statistics, University of Sussex, England
Dr. Anthony J Brookes, professor of genetics, University of Leicester, England
Dr. Helen Colhoun, ,professor of medical informatics and epidemiology, and public health physician, University of Edinburgh, Scotland
Dr. Angus Dalgleish, oncologist, infectious disease expert and professor, St. George’s Hospital Medical School, University of London, England
Dr. Sylvia Fogel, autism expert and psychiatrist at Massachusetts General Hospital and instructor at Harvard Medical School, USA
Dr. Eitan Friedman, professor of medicine, Tel-Aviv University, Israel
Dr. Uri Gavish, biomedical consultant, Israel
Dr. Motti Gerlic, professor of clinical microbiology and immunology, Tel Aviv University, Israel
Dr. Gabriela Gomes, mathematician studying infectious disease epidemiology, professor, University of Strathclyde, Scotland
Dr. Mike Hulme, professor of human geography, University of Cambridge, England
Dr. Michael Jackson, research fellow, School of Biological Sciences, University of Canterbury, New Zealand
Dr. Annie Janvier, professor of pediatrics and clinical ethics, Université de Montréal and Sainte-Justine University Medical Centre, Canada
Dr. David Katz, physician and president, True Health Initiative, and founder of the Yale University Prevention Research Center, USA
Dr. Andrius Kavaliunas, epidemiologist and assistant professor at Karolinska Institute, Sweden
Dr. Laura Lazzeroni, professor of psychiatry and behavioral sciences and of biomedical data science, Stanford University Medical School, USA
Dr. Michael Levitt, biophysicist and professor of structural biology, Stanford University, USA.
Recipient of the 2013 Nobel Prize in Chemistry.
Dr. David Livermore, microbiologist, infectious disease epidemiologist and professor, University of East Anglia, England
Dr. Jonas Ludvigsson, pediatrician, epidemiologist and professor at Karolinska Institute and senior physician at Örebro University Hospital, Sweden
Dr. Paul McKeigue, physician, disease modeler and professor of epidemiology and public health, University of Edinburgh, Scotland
Dr. Cody Meissner, professor of pediatrics, expert on vaccine development, efficacy, and safety. Tufts University School of Medicine, USA
Dr. Ariel Munitz, professor of clinical microbiology and immunology, Tel Aviv University, Israel
Dr. Yaz Gulnur Muradoglu, professor of finance, director of the Behavioural Finance Working Group, Queen Mary University of London, England
Dr. Partha P. Majumder, professor and founder of the National Institute of Biomedical Genomics, Kalyani, India
Dr. Udi Qimron, professor of clinical microbiology and immunology, Tel Aviv University, Israel
Dr. Matthew Ratcliffe, professor of philosophy, specializing in philosophy of mental health, University of York, England
Dr. Mario Recker, malaria researcher and associate professor, University of Exeter, England
Dr. Eyal Shahar, physician, epidemiologist and professor (emeritus) of public health, University of Arizona, USA
Dr. Karol Sikora MA, physician, oncologist, and professor of medicine at the University of Buckingham, England
Dr. Matthew Strauss, critical care physician and assistant professor of medicine, Queen’s University, Canada
Dr. Rodney Sturdivant, infectious disease scientist and associate professor of biostatistics, Baylor University, USA
Dr. Simon Thornley, epidemiologist and biostatistician, University of Auckland, New Zealand
Dr. Ellen Townsend, professor of psychology, head of the Self-Harm Research Group, University of Nottingham, England
Dr. Lisa White, professor of modelling and epidemiology, Oxford University, England
Dr. Simon Wood, biostatistician and professor, University of Edinburgh, Scotland
==================================================================
2) this speech has 1.2M views, 50k likes... in a week
it seems the facade is starting to crumble ... if suits
start to be instituted around the globe, one might predict that in a
month's time, the scam would be fully discredited. A monumental
development indeed...
3)Calif. doctor successfully cures 1,700 COVID-19 patients
4) This article by an eminent scientist who is no anti-vaxxer, discusses 4 of the major vaccine candidates:
Source: Covid-19 Vaccine Protocols Reveal That Trials Are Designed To Succeed
Because phase III trials won't be complete until late 2022, the plan seems to be to release the vaccines after interim trials for which the efficacy bar has been set very low indeed. They are required to be 70% effective at eliminating symptoms in around 50 PCR-positive subjects, out of thousands who receive the trial vaccine. The symptoms concerned can be very mild.
So, not only are the normal safety tests to be cut short, but the vaccines are not required to have any effect on anything that people are actually concerned about, such as:
- hospitalisation
- death
- durability of immunity (concerns have been raised by some about the durability of naturally-acquired immunity)
- being infectious while asymptomatic
- testing positive in a PCR test
- Long COVID or other complications
As the author says, "It boggles the mind and defies common sense that the National Institute of Health, the Center for Disease Control, the National Institute of Allergy and Infectious Disease, and the rest would consider the approval of a vaccine that would be distributed to hundreds of millions on such slender threads of success."
5) Some quotes from Dr David Nabarro, the WHO’s Special Envoy on Covid-19:
“We in the WHO do not advocate lockdowns as a primary means of controlling this virus.”
“We really do appeal to all world leaders: stop using lockdown as your primary control method”
“Lockdowns just have one consequence that you must never ever belittle, and that is, making poor people an awful lot poorer”
2020年9月29日星期二
《經濟一週》專訪:疫情影響深遠 外交戰雲密布 入市戒急用忍 20200929
聲明:所有傳媒發布的訪問內容只代表撰文者之理解,可能與本博客作者的分析或結論不同,或存有偏差
下為 二O二O年九月二十六日刊於《經濟一週》之封面專訪。
──────────────────────────────────────────────────
私募基金Bricks & Mortar Management主席王震宇曾被視為香港樓市的「大好友」,近年卻身體力行沽貨,論點更愈來愈淡,直言封城、封關引發的是經瀆大蕭條明年今日將有大量人口失業、大量公司倒閉、失業救濟金比目前至少翻倍,各地政府無法平衡預算。
更甚者,他指出目前南中國海點起狼煙,如果打得成,香港隨時有過百萬人離開。 此外,日、韓、美國都有政策鼓勵企業將生產線搬回當地,香港的出口地位搖搖欲墜,這些外部問題在短時開內難以逆轉。
基於前景不明朗,他建議有意入市者不要太「勇武」,以為「有個95折就有賺頭,隨時跌多三至四成都有可能。」
---------------------------------------------------------------------------------------------------------
樓價居高不下— BNO移民人數成最後一根稻草
本地樓價在疫情後陰跌成勢,儘管不如市股暴跌,令投資者觸目驚心,但有經驗的投資者都明白「陰跌才是最傷」。自2019件中原城市領先指數見頂收報189.42點後,目前指數已經累跌7%,但不少評論員仍聲稱樓市依舊堅挺,私募基金Bricks & Mortar Management 主席王震宇就直言,目前樓市存在無視供求面的大跌風險,「趕住買樓都要睇定啲先」。
他指出,目前經歷反送中運動及訂立《國安法》後,市民有關移民的查詢數量暴增,反映港人在回歸後,面對一波又一波的政治衝擊感到恐慌;而一眾西方國家亦因應《國安法》的落實,推出為港人度身訂造的移民或庇護方案(見圖表一)。

賣樓移民如同「潑出去的水」
大部分有能力移民至西方發達國家的市民都有不俗的經濟實力。「(香港樓市)隨時唔見咁一批生力軍,如果當中有10,000個家庭因為移民而拋售持有的物業,以現時每月平均4,000宗成交個案來計,已經是一季的總數。
雖則現時有不少人聲稱新供應量減少,但面對有一大班急著買摟的業主,即使未來「新供應」減少,但移民會否令「舊供應」蜂湧而出,是希望置業人士必不可少的考量。
王震宇補充,這班人賣樓移民後不會在市場買回物業,等於白白流失一大班有能力置業人士的購買力。
失業問題同樣是影響樓市需求的一大因素,環球封城令經濟下滑幅度及失業率。從單位數升至雙位數,而這次封關引發的大蕭條與過往的經濟衰退不同。 
私募基金Bricks & Mortar Management主席王震宇
「之前衰退可能是由100個消費者減到60個,但這次一直插到零,只要抵受唔住六個月,你就破產,玩完了。即使重開關口,你無本無人、無鋪、無產品去營運一門生意,其實都無用。」
他指出新冠疫情對全球經濟是一個影響久遠的打擊(Permanent hit)。
補貼救得一時教不了一世
他補充,疫情對經濟的打擊無遠弗屆,香港的保就業措施只是「吊鹽水」,「三個月、六個月的援助一停,沒有生意的企業始終都會執笠,就像國泰航空(00293),你畀錢佢,佢都寧願唔要,炒人算。」
他認為,最大的一波解僱潮仍未開始,但失業率已經達到6.1%,就業不足率亦升至3.8% 所以這次的失業率大機率高於「沙士」時期,而且高出不少。
除了本地的剛需下跌外,外在的環球政經環境同樣未許樂觀。他笑言:「上年就睇催淚煙,今年就睇南中國海及台海的硝煙。」這已經是一大拖累樓市的因素。如果前境不明朗,令有意上樓的人都「諗過度過」,需求又會再下跌。
內地資金逃離速度倍於港人
「香港點都好,都係要靠中國經濟食飯」,以前內地經過香港出口,香港擔當中轉站角色,內地人賺到的外匯就會在香港消費,當中就包括投資物業,但兩者均正在快速消失。
而外國從內地撤資,日本、南韓、美國都有政策,鼓勵企業將生產線搬回本國,香港的出口地位自然搖搖欲墜,更惶論現時中美角力令香港變成磨心。
而以上的一切外部問題,在短時間內難以得到根本逆轉。「情況只會愈來愈差,面對這發生的一切真是難以樂觀。」
近來的本地政治事件,令內地人對香港地位的看法亦有改變。「以前內地人將錢放在香港是因為香港異於內地,依家咁搞法,(內地人)分分鐘走佬走得快過香港人,聽日有咩風吹草動沽左樓就走咗去。」
他指出,內地投資者在港多數以空般公司買物業,「借足10次金蟬脫般連樓都唔駛賣,你香港人走佬,仲要等英聯邦公開移民政策再賣樓,邊夠人快?」
他猜測明年英國開放BNO申請長期居留會吸引一批人移民離港,「會有幾千、幾萬、幾十萬個人離開香港? 依家無人會知,但這批人在明年一定會對樓市產生大波動。」
中西惡鬥港移民難民一線之分
他指出目前南中國海點起狠煙,如果打得成,香港明年隨時有過百萬人離開到時候假設每三個人賣一間樓都足足有30萬以上個單位供市場消化。而根據過往的年均物業成交量,相信需要五年以上時間消化,甚至出現「人踩人的狀況」。當然,如果中美出現大和解,可能只有數百人離開香港,但這是後話了。
不過現時前景不明朗,不應該「勇武衝入去買樓,以為比起高位有個95折就有賺頭,但隨時跌多三至四成都有可能發生。」
兩大數據警示樓市大轉角
(一) 債務危機
這一次由疫情引發的經濟大蕭條,令大量國家的財政儲備所剩無幾。「明年今日大量人口失業,大量公司倒閉,失業救濟金比起目前起碼翻倍。以前3%失業率需要1%的GDP金額去援助,如果明年失業率飆升至20%,政府的財政就玩完了,完全無法平衝政府預算。」
他推算到時候各國政府的債務水平亦會拉升,這亦是現時不少國家推行電子貨幣取代現金的理由。
「現金拿去外國兌換走了就駟馬難追,但如果是電子貨幣,只要政府一聲令下,銀行就能即時扣除資本稅,想避都無得避。」
這是一個政權遇上財務問題的一大徵兆:歐洲各國已經積極商討,內地更直接試行,美國亦開始討論,所以即使政府債務再高,只要貨幣電子化,想如何開展資本稅或是負利率也可以。
王震宇指出目前種種跡象證明各國政府正積極「取富於民」,如果要錯開資本稅,只有兩個方法,第一會是將資產分配至未有執行相關政策的國家,第二就是投資實物資產,包括股票、房地產及已經因疫情被大量拋售的大宗商品。
各國為了應對疫情而大「印銀紙」,延後債務危機的爆煲時間,將未來的回報提前享用,但總有一天紙包不住火,所有息口抽升,一些高槓桿的投資便會立即翻船。
所以未來投資一定要選擇一個低槓桿市場, 但香港作為一個金融中心,恰恰就是全球其中一個最高槓桿的市場。
(二) 居屋申讀數早於樓價見頂
王震宇引用數據,指出每當居屋的申請倍數超購70倍,往往預示樓市已經見頂,但市面上的政客顛倒黑白,訛稱供應不足才令申請人數破頂,這種短視的思維令買入居屋的小市民「蟹咗」。
他多年來積極反對興建居屋,反對用公共資源引導市民在錯誤的時機入市,造就大量負資產,他認為不應該因為樓市供應不足,而無視可能引起負資產的問題。

尋找投資「轉角位」
數據發掘英國移民寶地
王震宇看淡香港樓市的其中一個主因是預期將有大批人移民,而提到移民,放寬移民政策的英國相信是不少港人的首選。
至於移民是否應該買摟,買樓又該如何選擇地區,又是另一大課題。他指:「要在英國落腳很容易,香港賣一層樓都1,000萬,在英國可以買到三間,問題是你個人能否適應當地環境、文化等因素。」本文將致力探討英國物業投資策略,有計劇移民的讀者可作參考。
研究機構料英國樓價回調14%
繼英國放寬BNO持有人權利後,移民英國及置業就一直成為大眾的焦貼。回看英國樓市,據英國Halifax銀行的數據,英國樓價於8月按月上升1.6%,按年升幅為5.2%,為英國樓價自 2016年底以來的最高水平:而英國平均樓價更破紀錄,升至24.5萬英鎊(約245萬港元)。
英國樓價「疫市」上升,不少報告都警告這是見頂訊號,根據英國智庫經濟及商業研究中心(Centre for Economic and Business Research, CEBR)研究報告指,英國樓價飆升只屬暫時性,更預期樓市泡沫將於明年爆破,樓價有可能大跌13.8%。
CEBR指英國樓最近成交活躍,主要是因為英國政府推出減免印花稅指施,約翰遜政府在 7月宣布,將豁兔印花稅至明年3月,首次置業人士購入50萬英鎊(約509萬港元)或以下物業時,毋須支付印花稅。
不過,報告指出英國因早前封城而擠壓房地產市場購買力,受疫情影響,今年3月至6月間,有近15萬宗交易被擱置,隨著疫情緩和將慢慢釋放購買力。
對於英國樓價近期的震盪,王震宇就表示: 「作為一個投資者就應該理性判斷一個市場蓬勃了十年,不代表未來十年也一樣興盛,這是典型的線性思維。」
他續指:「其實投資最難就是找『轉角位』 我們研究的市場大多都是剛進入轉角位,但凡一個市場能成為大家茶餘飯後的話題時,該市場的轉角位就已經進入頂部。」
他又以Airbnb來補充上述論點:「未封關前全世界都爭著做Airbnb因為yield spread(利差)夠勁,借2里可以收到5里回報,諗住借到盡做實無死。奈何一個疫情殺到,回報變成零,2里利息都還不起,市場就一窩蜂將樓盤拋出來。」
若然英國樓價將在明年開始下降,有心入市的投資者該如何部署?王震宇勸喻投資者入市前多做功課,不要盲目信從經紀公司的資訊。
「要判斷一個區域是否值得投資有很多標準可參考,例如宏觀經濟、基建建設、人口增長等,總之不要只信廣告的資訊。五年前很多廣告吹捧 South Bank、 Nine Elms這些地區。你要是當時跟風買入就蝕了四、五成,我們是以數據去看一個地方的潛力。」
倫敦、漢普郡住屋升值潛力大
至於英國現時有甚麼地區較有潛力?在放寬 BNO簽證權政策下,有機會影響英國各區的住屋的需求,而各地樓價的受惠程度亦有分別。
評估港人如何選擇落腳點的方法眾多,根據王震宇提供的數據。是採用了現時英國各區華人分布量做參考,,繼而估計港人選擇移民的地點。
不過此方法有機會存在些少誤差,因為當地華人分布受不同歷史因素影響。新來者未必會按既有比例選擇居住地區,但相信大城市依然會是港人移民的首選地點。
據數據顯示(見圖表三),內倫敦、外倫敦及諾定咸是現時英國華人人口叢多的三個地方,分別為65,983人、58,267人及5,988人;而華人佔各地區總人口百分比的數字,內倫敦、諾定咸及修咸頓則有著較高的佔比。

現時在英國的華人數目約為43.3萬人。而估計擁有合資格BNO的港人為300萬名,所以只要有一成合資格港人移居英國當地的華人數目將從現在的43.3增多30萬人即飆升70%;而當這30萬名港人栘居英國後,華人的比重將會由 0.7%飛升到1.2%。
現時的華人聚居地已某程度上反映華人群組的生活習性及喜好。而假設港人會按目前華人分布的比例移居英國(見圓表四)。大倫敦、大曼徹斯特、漢普郡、諾定咸郡、薩里郡為最多華人的五個地區。

假設有30萬人港人移居英國,現有的空置房屋將合是首先被購買入住的目標。在此情況下,漢普郡、倫敦及諾定咸的樓盤量將最先面對嚴重供不應求的局面(見圖表五)。

在漢普郡(不包括修咸頓及樸茨茅夫,圖表五中1號點)平均3.32個BNO持有人要爭奪一個空置房屋;而內倫敦及外倫敦(圖中2及3號點)亦是現有房屋比較緊張的地區,亦是圖表五中Y軸值大於1的地區。
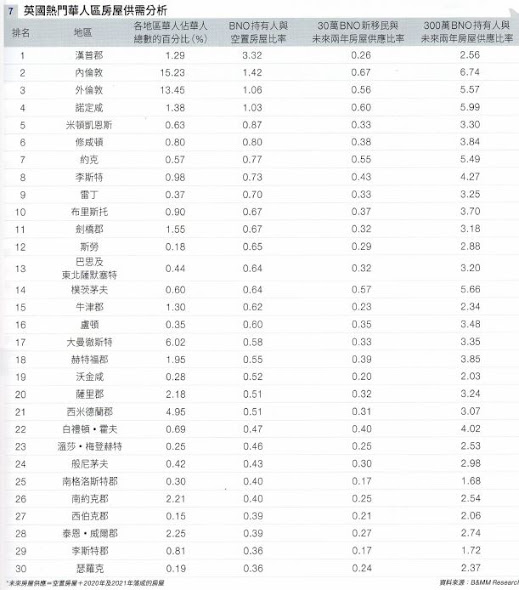
當假設300萬名合資格BNO持有人在英國置業,如未來兩年能維持2019年的新房落成量,即使涵蓋未來兩年的新供應,市場樓盤的供應量依然持續緊張(見圖表六)。

當中,住房最緊張的地方為倫敦(圖表六中 2及3號點)、約克(4 號點)、樸茨茅夫(14號點) 及諾定咸C7號點)。
而從圖表七中的數據顯示,若全數BNO合資格的港人移居英國,內倫敦及外倫敦的供求比會暴漲至6.74倍及5.57倍。
總結來說,結合以上的數據分析,隨著放寬 BNO簽證權的政策,吸引港人移民英國,熱門地區的樓宇需求將會倍升,而該地區樓價相信亦會跟隨攀升。若然投資者有準備入市,可多加留意上述分析的熱門地區。
原文見《兩大警示樓價大跌 移民政策將失大批新力軍 王震宇:買樓要睇定啲》
訂閱:
文章 (Atom)